Opioid addiction among older Ontarians more than doubled over past decade, study finds

The number of older Ontarians living with opioid use disorder has more than doubled over the past decade, according to new research that highlights how the country is not currently equipped to support this growing population. MAP scientist Dr. Tara Gomes, who co-lead the research, spoke with The Globe and Mail about the findings.

This story was also covered in the Toronto Star, CTV News, CP24 and Global News.

His addiction started with a toothache. Why Ontario’s older adults are facing an ‘overlooked and evolving’ opioid crisis

MAP scientist Dr. Tara Gomes spoke with the Toronto Star about new research that found that number of Ontarians aged 55 and older with healthcare interactions related to opioid use disorder (OUD) has more than doubled in Ontario between 2017 and 2025.

This story was also covered in Globe and Mail, CTV News, CP24 and Global News.

Number of older adults living with opioid use disorder in Ontario more than doubles over eight years, new report finds 

The number of Ontarians aged 55 and older with healthcare interactions related to opioid use disorder (OUD) has more than doubled in Ontario between 2017 and 2025, according to a new report published by the Ontario Drug Policy Research Network (ODPRN), based at St. Michael’s Hospital.

Key findings

  • The number of older adults engaging with the healthcare system about OUD grew from 7,116 people in 2017 to 15,231 people in 2025. In contrast, the number of older adults with OUD living in Long-Term Care (LTC) remained low (<130) and stable over the same period.
  • Use of opioid agonist treatment (OAT) more than tripled between 2013 and 2025, rising from 2,661 to 13,370 recipients.
  • Opioid toxicity death rates increased substantially between 2013 and 2024, peaking during the COVID-19 pandemic — with over 1,000 older adults dying of an opioid toxicity between 2023-24 alone.
  • The unregulated drug supply played a growing role in deaths, with fentanyl’s involvement in opioid toxicity deaths doubling from 31 per cent of deaths in 2017 to 62 per cent 2024.
  • There were 1,087 opioid toxicity deaths among older adults in 2023 and 2024, the equivalent of at least one death every day. Of these, 985 deaths could be linked to other healthcare records. Among these deaths:
    • Nearly 75 per cent occurred among people aged 55 to 64.
    • About 80 per cent occurred in a private residence, and only one in five occurred with someone present who could intervene.
    • More than half lived with a pain condition in the years before they died.
    • Only one-third involved prescribed opioids only, although this increased with age.
    • A quarter had a healthcare visit in the week before death, and 1 in 4 had received home care in the year before death

How they did it

Tara Gomes, PhD and Bisola Hamzat, MSc authored the report in collaboration with community partners and people with lived experience, drawing on population-based health-care data from ICES.

They used several datasets from ICES to identify older adults with OUD and opioid related deaths, including hospital and home care databases, coroners’ death investigations, and pharmacy dispensing data.

Why it matters          

As the population living with OUD ages, healthcare and social services need to be prepared to provide care that addresses the complex care needs of this population, expertise that the system may currently lack.

Only 38 per cent of older adults who died of an opioid toxicity had engaged with the healthcare system around OUD in the past five years, below the more than 50 per cent seen in the general provincial population. Despite this, 1 in 4 had some contact with the healthcare system in the week before death.

Hamzat says, “What stands out is how many of older adults weren’t in contact with the health system for opioid use disorder before they died. With many older adults disengaged from medical care for substance use, responses that integrate both harm reduction, treatment services, and social supports that are accessible for a population with age-related needs remain imperative”.

Despite rapidly growing OUD among older adults, very few people were in LTC, and this didn’t change over time. In contrast, home care services in the year before an opioid toxicity death were higher, suggesting more community-based support in this population.

“Older adults with opioid use disorder aren’t in long-term care, they’re at home, often relying on home care services right up until a fatal overdose.” Says Gomes. “However, these sectors are often under-equipped to provide the best possible care to this population. Both the long-term care and home care sectors need to build the staff expertise and flexible, accessible supports that consider mobility issues, transportation barriers, disability, and pain management needs to actually reach and adequately support this growing and often invisible population”

The report recommends stronger education and awareness for older adults, their doctors, caregivers and families on recognizing and discussing substance use and knowing how to respond to an opioid toxicity.

Gomes adds, “I hope this report helps start a broader discussion about how our healthcare system can better identify and support older adults at risk of drug-related harms at critical points in their care, through enhanced screening and stronger expertise in substance use care”

What’s next

The findings highlight the urgency for health and social service systems to prepare now for an older population with OUD that will keep growing. That means building tailored, age-sensitive programs and supports, using existing points of contact to identify risk earlier, and designing supports that are accessible to older adults.

Read the full report here

By Zehra Goawala

Ottawa announces $5M for HIV self-test kits, peer support with St. Michael’s Hospital to play critical role

Dr. Sean B. Rourke, director of REACH Nexus at St. Michael’s Hospital’s MAP Centre For Urban Health Solutions helped secure the approval for both HIV self-tests available in Canada. (Photo: Eduardo Lima/Canadian Press)

The federal government has announced $5 million in funding for HIV self-testing, prevention and support services, with St. Michael’s hospital playing an important role in distributing 100,000 HIV self-tests to people who need them.

The announcement was made Thursday in Winnipeg by Dr. Joss Reimer, Canada’s chief public health officer, as Manitoba responds to HIV rates that are three times higher than the national average and has declared a public health emergency.

Dr. Reimer said advances in HIV treatment mean people living with HIV can live long, healthy lives, but knowing your HIV status remains the essential first step to accessing treatment, care and support.

“By expanding access to HIV self-test kits and community-based peer support, this investment will help more people receive an earlier diagnosis and connect with the treatment and prevention services that meet their needs—particularly in communities most affected by HIV,” she said.

Of the $5 million announced Thursday, $2 million will be used to purchase 100,000 OraQuick HIV self-test kits. OraQuick is Canada’s first approved oral-fluid HIV self-test. REACH Nexus, a research organization at St. Michael’s Hospital’s MAP Centre for Urban Health Solutions, led the clinical trials that helped get Health Canada’s approval of the test, announced earlier this year.

St. Michael’s Hospital is the exclusive distributor of OraQuick in Canada and will work with the federal and Manitoba governments and frontline agencies to ensure the self-tests reach people and communities that face the greatest barriers to testing.

Dr. Sean B. Rourke, director of REACH Nexus, called the new funding a “meaningful advancement in Canada’s efforts to end HIV/AIDS.” He said expanding access to HIV self-testing and peer-based support is particularly important for communities disproportionately affected by HIV, including Indigenous, Black and other racialized populations.

“Real health innovation means meeting people where they are and removing the barriers that stand between them and care,” said Dr. Rourke. “By bringing testing, prevention and care directly to people, we can reach communities too often left behind by traditional healthcare—and give everyone the opportunity to know their status, protect their health and access the care they need.”

The OraQuick HIV Self-Test uses a simple oral-fluid swab and delivers results in 20 minutes with over 99% accuracy. (Supplied photo)

Dr. Rourke and his team at REACH Nexus also led the clinical trials that helped Canada’s first HIV self-test receive regulatory approval in 2020. In 2021, during the COVID-19 pandemic, Rourke launched I’m Ready, a national HIV self-testing program that has since distributed more than 36,000 free HIV self-test kits across Canada and connected thousands of people to prevention, treatment and care.

He also previously led Community Link, a federally funded program that expanded access to HIV self-testing across Canada. Together, these initiatives have helped make low-barrier HIV self-testing available to more than 100,000 people.

The remaining $3 million in new funding will support peer workers, who will help connect people to testing, prevention and treatment services.

Shohan Illsley, executive director of the Manitoba Harm Reduction Network, said significant barriers continue to prevent people from accessing HIV testing and treatment.

“Expanding access to HIV self-tests and peer support services will help improve access to low-barrier testing, particularly in rural, remote and northern communities where stigma can have a significant impact on access to testing and linkage to HIV care,” she said.

The federal government says 2,300 new HIV diagnoses were reported in Canada in 2024, while an estimated 7,000 people are living with HIV without knowing their status.

By: Andrew Russell

Homelessness Navigator pilot in Fredericton supports safer transitions from hospital

A new pilot program aimed at helping unhoused people transition safely back into the community after admissions at the Dr. Everett Chalmers Regional Hospital in Fredericton, New Brunswick is yielding positive results, the Horizon Health Network reports. The pilot program is modelled after MAP’s Navigator program at St. Michael’s Hospital in Toronto, whose staff have visited the Fredericton facility and consulted on the local navigator project.

‘We are not these vectors of disease anymore,’ New campaign takes aim at HIV stigma

The ‘Just Say It!’ campaign from MAP’s REACH Nexus has now generated more than 2 million views on social media, helping to spark meaningful conversations about HIV, testing, relationships, U=U and stigma.

MAP’s James Watson spoke with NOW Toronto about the importance of reaching people beyond existing HIV organizations and communities when it comes to breaking down stigma.

They’re well enough to leave, but have nowhere to go. Why homeless patients get stuck in hospital — and one plan to help fix it

A recent study led by Lucie Richard, MAP adjunct scientist, found that homeless people in Ontario are 4.5 times more likely to stay in hospital after they’re well enough to leave, a designation called alternate level of care, when compared to counterparts from low-resource neighbourhoods. This highlights the lack of post-acute care options for patients experiencing homelessness, a gap that shelters are not designed to fill.

Lucie and Dr. Stephen Hwang spoke with the Toronto Star about the findings and how Ontario hospitals are expanding their scope to support these patients. They shared plans for St. Michael’s approximately 16-bed recuperative health space for patients who are homeless and staying in hospitals with complex recovery needs, slated for early 2027.

Opioid deaths are down but emergency calls are spiking. Inside the mystery leaving Ontario paramedics ‘flying blind’

MAP scientist Dr. Tara Gomes is quoted in Toronto Star about health concerns related to the drug poisoning crisis. Hayley Thompson, project manager of Toronto Drug Checking Service, is also mentioned, reporting that the average amount of medetomidine (an animal tranquilize) found in fentanyl samples has increased in the past year.

New research affirms construction workers disproportionately affected by opioid deaths

A new study lead by MAP scientist Dr. Tara Gomes, found that construction and trades workers accounted for approximately one-third of opioid toxicity deaths in Ontario where occupation was known between 2018 and 2024.

“I think a lot of people have a picture in their mind as to the opioid toxicity crisis, who is experiencing loss of life,” Dr. Gomes told The Canadian Press, adding that in some cases there may be a link between people’s overdose use and their working conditions.

This piece was also published in the Toronto Star.

Rates of opioid toxicity deaths highest among construction and trades workers, study finds 

  • ODPRN analysis of trends in opioid toxicity deaths among Ontario workers finds impacts across sectors, with some particularly hard hit 
  • Between 2018 and 2024, those who worked in construction and trades made up approximately one third of deaths from opioid toxicity in Ontario where occupation was known 
  • People who worked in manufacturing, hospitality and retail each made up close to 10 per cent of these deaths. 

Between 2018 and 2024, those who worked in construction and trades made up approximately one third of deaths from opioid toxicity in Ontario where occupation was known, according to a report released this week by the Ontario Drug Policy Research Network (ODPRN). In addition to highlighting the toll of opioid toxicities in this sector, the report also draws attention to the impact of opioid toxicities among people across various occupations. 

“People across every walk of life and every kind of job are affected by opioid toxicity, though the circumstances behind those deaths and how we might prevent them are nuanced and often differ from one workplace to the next,” says Shaleesa Ledlie, senior research associate at the ODPRN, a research group based out of St. Michael’s Hospital and Unity Health Toronto and lead author of the study. “It’s helpful for us to understand who is most affected and how, so we can tailor approaches and services to the specific needs of different people and workplaces.”  

Read more about this in the Canadian Press 

The ODPRN team used population-based health care data from ICES, a non-profit research institute that uses health data to produce knowledge on a broad range of health care issues. They used this data to examine the trends and circumstances surrounding opioid toxicity deaths among different employment sectors in Ontario from January 1, 2018, to December 31, 2024. 

During this period, there were nearly 16,000 deaths in Ontario from opioid toxicity; approximately 3,500 of these people had an occupation included in the coroner’s report and were included in the study. The study showed that different employment sectors were affected differently by opioid toxicities, with varying rates of toxicities, trends over time and circumstances of death. 

The construction and trades sector was particularly affected, with not only the highest rates of death, but also increasing rates of death over the study period. 

“Our findings show that opioid-related deaths are not affecting all workers equally. Specifically, people working in industries such as construction, trades and mining experienced the highest rates of opioid-related deaths, with these deaths increasing considerably during the COVID-19 pandemic and remaining elevated over time,” says Tara Gomes, senior author of the report, a scientist at MAP Centre for Urban Health Solutions at St. Michael’s Hospital and ICES, a principal Investigator of the ODPRN, and a Professor (status) at the Leslie Dan Faculty of Pharmacy at the University of Toronto. “The reasons for this are likely multifaceted, including these occupations being male-dominated fields where people are at risk of injuries, undertreated pain, difficulty accessing treatment and barriers to discussing substance use.”  

Andrzej Celinski is a co-author on the study and co-founder of the Reclaim Collective, an organization of people with lived experience that provides education and consulting services related to issues such as substance use, harm reduction, and housing insecurity.  

Celinski has previously worked in the construction industry and is currently a board member for the Workers for Ethical Substance Use Policy. He says, based on his lived experience, the high rates of toxicities among workers in construction and trades was not surprising, and that workplaces could take on a greater role in harm reduction. 

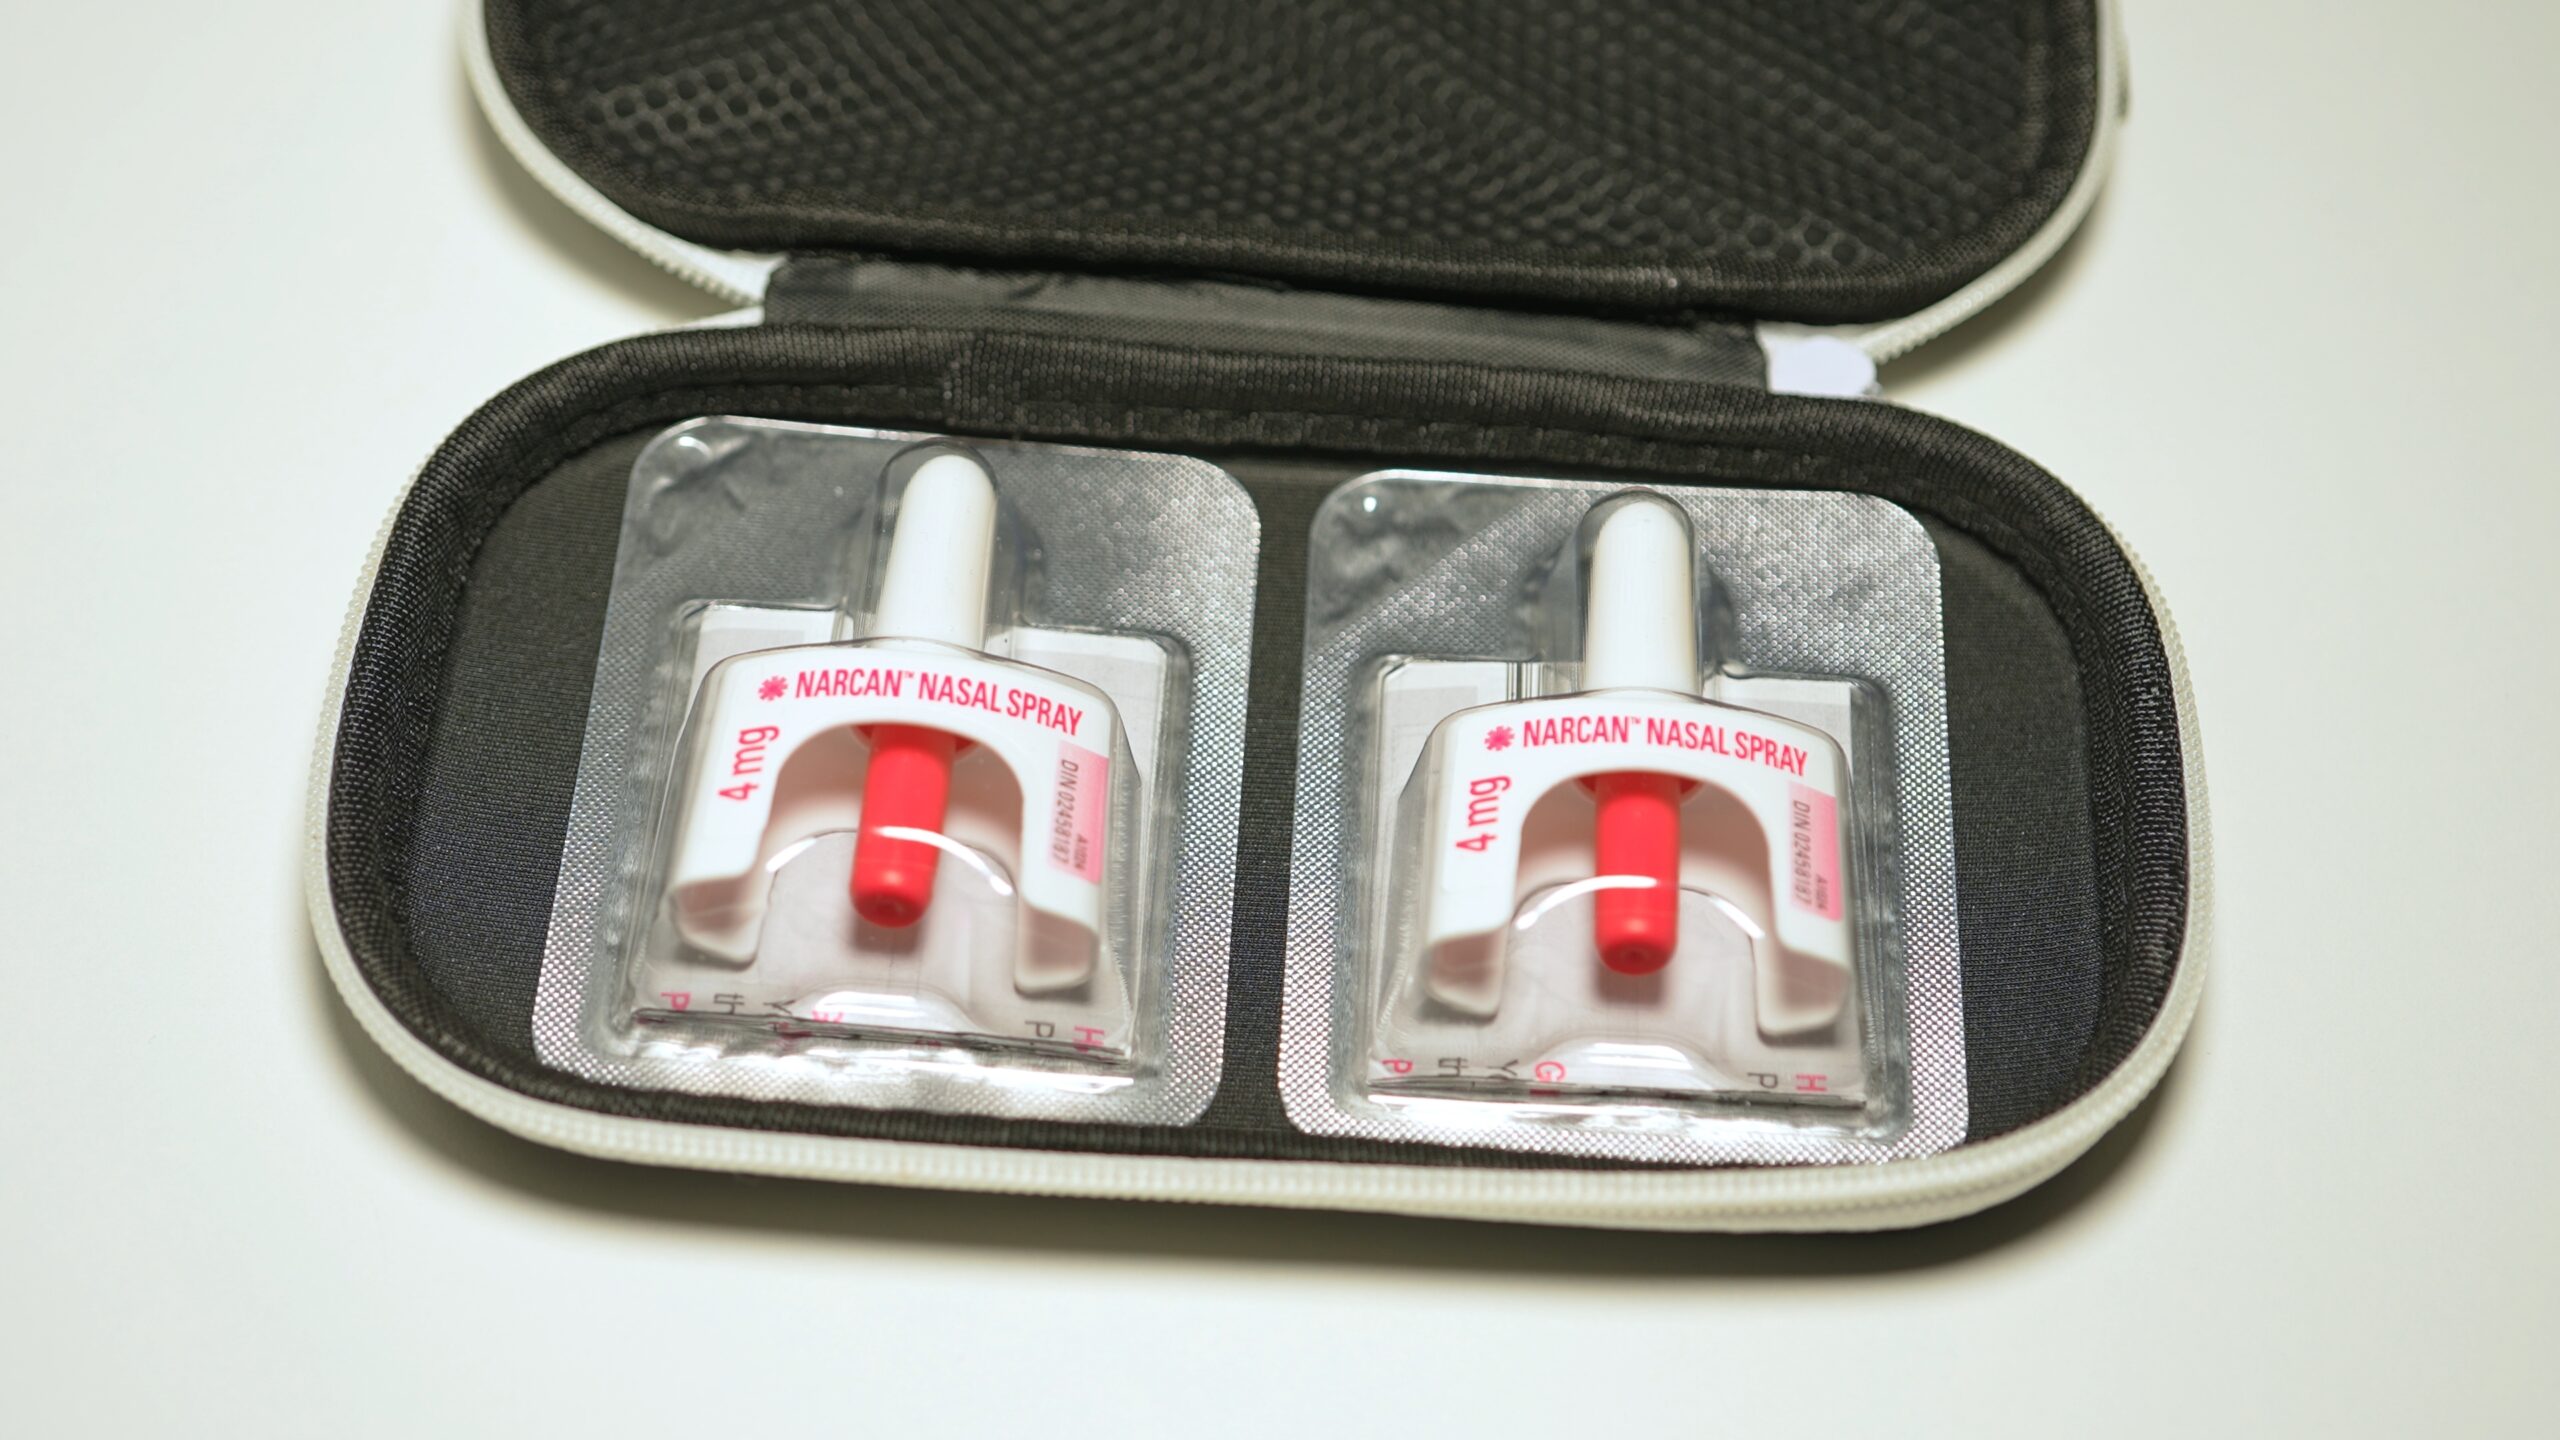
“Drug use in the workplace, specifically construction and trades, doesn’t get addressed very well. It’s a workplace shaped by physically demanding work, injuries and chronic pain, and a culture where asking for help can feel risky. The workplace needs to feel safe enough for people to ask for support before things become too difficult to manage on their own and they feel they have nowhere else to turn,” he says. “Making naloxone, overdose training or awareness, and connections to care more prominent in the workplace would help to reach people who might not access other traditional services, but this isn’t happening in most cases.”  

Analysis points to need for tailored programs and services that address underlying factors 

Other occupational sectors were also significantly affected by opioid toxicities. People who worked in manufacturing, hospitality and retail each made up close to 10 per cent of deaths. 

Rates of death among people who worked in civic and government services (e.g., police, military personnel and firefighters) increased over the study period, while rates for manufacturing and transportation, warehousing and equipment operations were consistently high. The researchers note that these roles are often physically demanding, with high rates of workplace injury, chronic pain, mental health challenges and lack of support to manage transition from pain medications – all of which may increase risk. 

Conversely, rates for other sectors – notably hospitality – peaked during the first years of the COVID-19 pandemic and have since decreased. 

Approximately one third of people who died were unemployed at the time of death, although the hospitality sector had a higher proportion of unemployment at time of death. The researchers say that this may reflect the impact of temporary layoffs, particularly in the hospitality sector during the pandemic; it may also suggest that loss of employment, and transitions from the workforce because of injury, pain or mental health challenges may increase people’s risk of substance-related harm. 

While most deaths were determined to be accidental, three sectors – civic and government services, healthcare, and administrative, financial and support services – had higher proportions of deaths by suicide. 

“Taken together, these findings reinforce the need for programs and services that are tailored to the diverse needs of people at risk of opioid-related harm,” says Gomes “While workplace-based prevention, education and support remain important, with most opioid-related deaths occurring in people’s homes, efforts must also extend beyond the workplace and include reducing stigma surrounding substance use and improving access to treatment and harm reduction services to better support people across the settings in which they live and work.” 

For example, underlying structural factors such as housing instability, income insecurity, and insufficient access to pain management and mental health care can all increase the risk of substance-related harm. As a result, many different harm reduction and treatment approaches are needed to keep people safe and address the underlying pain, trauma or mental challenges people experience. 

“Toxicity deaths are not happening in a vacuum or to a specific group of people. Not all overdoses are happening among folks who are unhoused or in public where people can see. Oftentimes, this is happening behind closed doors and in people’s houses, often when they are alone, so it’s invisible to the population,” says Celinski. 

“We need to look beyond individual behavior and address the conditions that shape folks’ ability to access support.” 

Adapted from an article by Eileen Hoftyzer, writer at the Leslie Dan Faculty of Pharmacy at University of Toronto 
Photos courtesy of University of Toronto, Leslie Dan Faculty of Pharmacy








